
The Panel Required at Diagnosis
Metastatic colorectal cancer is cancer that began in the colon or rectum and has spread to distant organs, most often the liver, lungs or peritoneum. A decade ago nearly every patient started the same way, with chemotherapy and an antibody against blood vessel growth. Today the first drug is chosen from the tumour's molecular profile, which ESMO asks to be known before treatment starts.
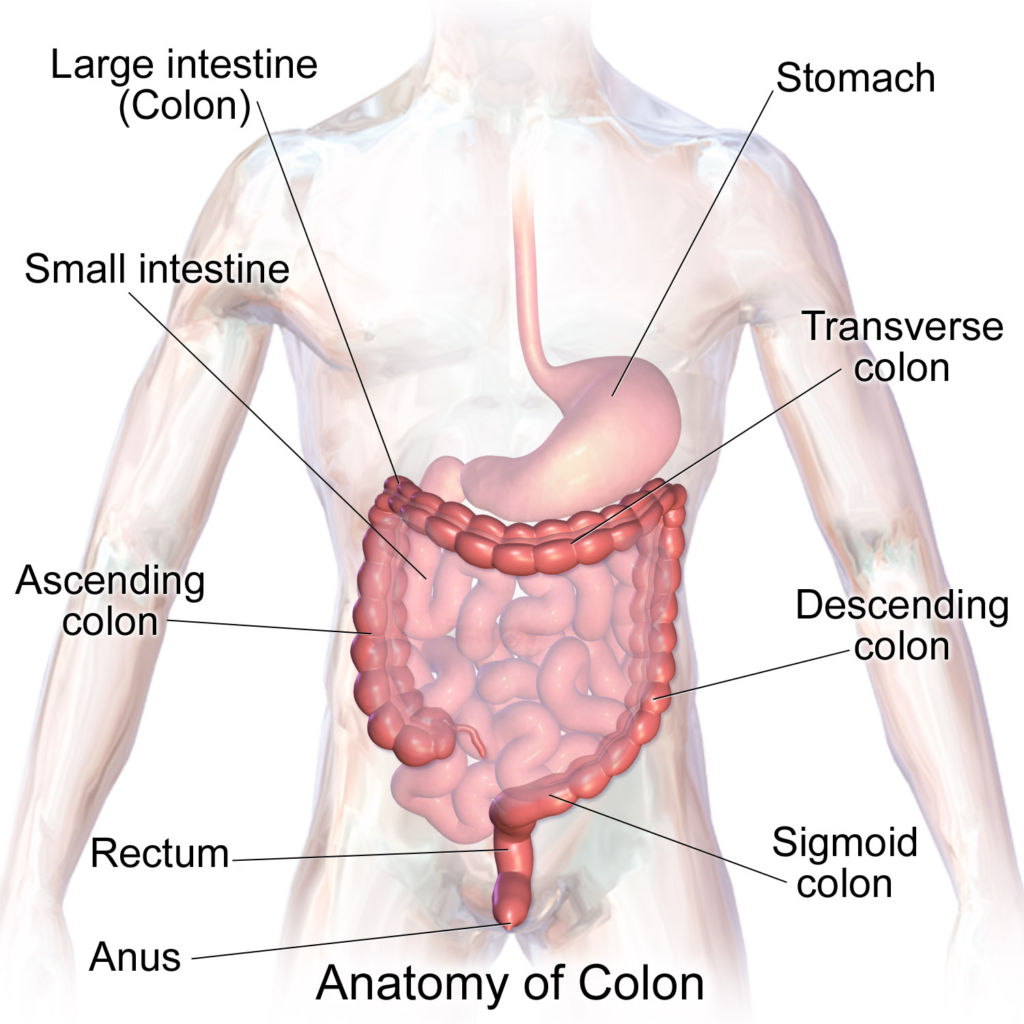
Four results are required at diagnosis:
- RAS (KRAS and NRAS) mutation
- Genes that relay the growth signal inside the cell. When mutated, anti-EGFR antibodies (cetuximab, panitumumab) do not work, so these drugs are reserved for RAS wild-type tumours. About half of metastatic patients carry a RAS mutation.
- BRAF V600E mutation
- Found in 8 to 10 percent of patients and associated with a more aggressive course. It now has a first-line treatment of its own.
- MMR / MSI status
- Loss of the DNA mismatch repair system (dMMR) or microsatellite instability-high (MSI-H) predicts benefit from immunotherapy. About 4 to 5 percent of metastatic patients fall into this group, and the finding can be the first clue to hereditary Lynch syndrome.
- HER2 Amplification
- Extra copies of the HER2 gene, in 3 to 5 percent of cases and mostly in RAS wild-type tumours. It opens the door to HER2-directed therapy and signals reduced benefit from anti-EGFR antibodies.
These results can come from separate tests or from a single NGS panel. The results are needed before the first-line decision, so testing is requested as soon as the diagnosis is confirmed. The testing process is described on the comprehensive genomic profiling page; the stages of the disease and the general approach to treatment are on the colorectal cancer page.
Why the First-Line Decision Is Ordered by Biomarker
Once the patient's fitness and the goal of treatment are defined (converting liver metastases to a resectable state, long-term disease control or symptom relief), the first-line algorithm works through the biomarkers in a set order. The order matters because some findings take precedence over others.
| Order | Biomarker result | Preferred first-line approach | Key evidence |
|---|---|---|---|
| 1 | dMMR / MSI-high | Immunotherapy: pembrolizumab, or nivolumab plus ipilimumab, instead of chemotherapy | KEYNOTE-177, CheckMate 8HW |
| 2 | BRAF V600E mutation (pMMR) | Encorafenib, cetuximab and FOLFOX; chemotherapy plus bevacizumab if unsuitable | BREAKWATER |
| 3 | RAS and BRAF wild-type, left-sided | Chemotherapy plus an anti-EGFR antibody (cetuximab or panitumumab) | PARADIGM |
| 4 | RAS-mutant or right-sided | Chemotherapy plus bevacizumab; triplet chemotherapy (FOLFOXIRI) in fit patients | TRIBE, FIRE-3 subgroup analyses |
| 5 | HER2-amplified (RAS wild-type) | Standard chemotherapy first line. HER2 amplification does not change the first-line chemotherapy backbone; it is recorded now and used at progression for HER2-directed therapy, and it is a reason to expect less benefit from an anti-EGFR antibody | MOUNTAINEER, DESTINY-CRC01 |
The logic runs as follows. dMMR/MSI-high tumours carry so many mutations that the immune system can recognise them, and checkpoint inhibitors outperform chemotherapy in this group by a wide margin, so the MMR question comes first. BRAF V600E did poorly on chemotherapy and now has a dedicated targeted combination, so it is asked second. For everyone else, RAS status and tumour side decide between an anti-EGFR antibody and bevacizumab. See the immunotherapy and targeted therapy pages for the principles behind each drug class.
Important: This article explains the principles of the ESMO guideline and its published updates in plain language; the full recommendations and their grades are in the guideline listed under Sources. Which option applies to a given patient depends on fitness, other illnesses and the licensing status of each drug in the country of treatment. Nothing here replaces a consultation with your own oncologist.
Left-Sided Versus Right-Sided Primary
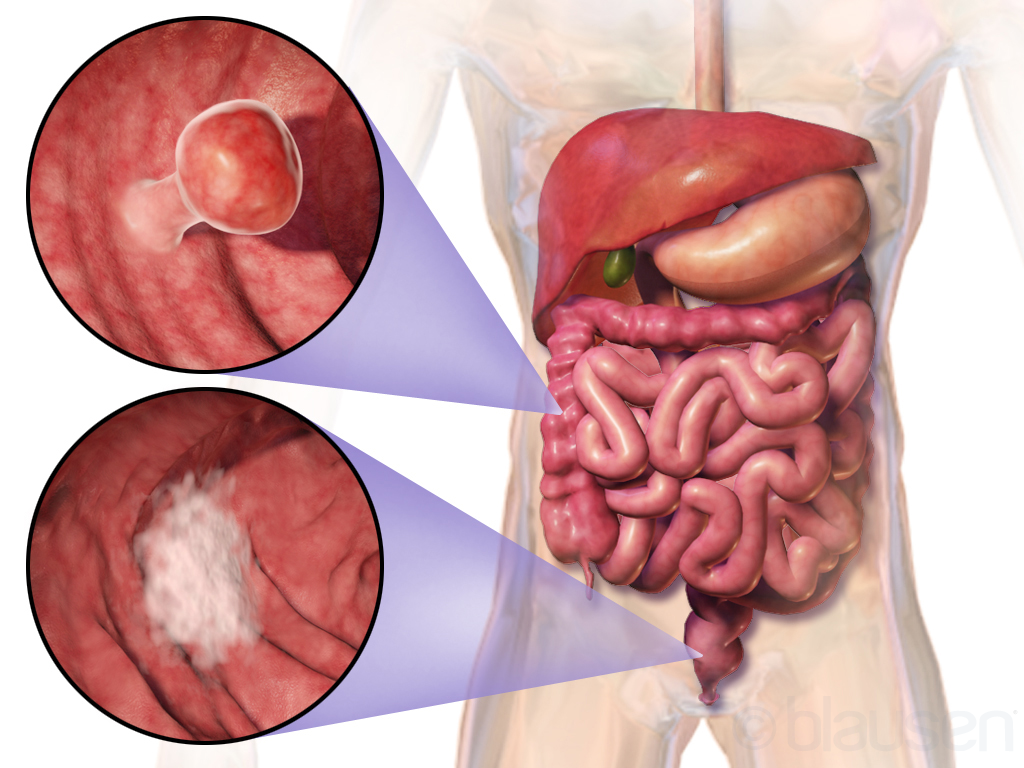
The right colon (caecum, ascending colon and the first part of the transverse colon) and the left colon (descending colon, sigmoid and rectum) develop from different embryonic tissue. Right-sided tumours more often carry BRAF mutations and MSI-high status; left-sided tumours more often show HER2 amplification and dependence on EGFR signalling.
This difference feeds directly into treatment. In RAS wild-type left-sided disease, the PARADIGM trial found that panitumumab with chemotherapy extended median overall survival to 37.9 months compared with 34.3 months for bevacizumab with chemotherapy. In right-sided tumours no such benefit from the anti-EGFR antibody was shown, and chemotherapy with bevacizumab is preferred. This is why the guideline does not treat "RAS wild-type" as sufficient on its own; it looks for "left-sided and RAS/BRAF wild-type" together.
Send Your Reports for Assessment
Share your pathology, imaging and blood results on WhatsApp, or send them by email. Documents are reviewed before the consultation.
BRAF V600E: Encorafenib, Cetuximab and Chemotherapy
For years, BRAF V600E-mutant metastatic colorectal cancer was treated with chemotherapy alone and had poorer outcomes than other subgroups. The BRAF inhibitor encorafenib with the anti-EGFR antibody cetuximab first showed benefit in second line (the BEACON trial). BREAKWATER then added this pair to FOLFOX chemotherapy in first line: adding encorafenib and cetuximab to FOLFOX improved the response rate and survival compared with chemotherapy alone (the response-rate result is reported in Kopetz et al., Nat Med 2025). Guidelines therefore list a BRAF-directed combination, encorafenib with cetuximab, added to chemotherapy as a first-line option for fit patients with BRAF V600E disease.
The side effects combine those of chemotherapy and targeted agents: acne-like rash, diarrhoea, fatigue, peripheral neuropathy and joint pain. Patients who cannot tolerate chemotherapy may receive encorafenib and cetuximab alone. Where BRAF V600E and dMMR occur together, immunotherapy takes priority.

Does Every Rectal Cancer Patient Need Surgery
Planning looks not only at where the tumour sits but at its molecular features; the video explains how findings such as MSI-H can change the decision.
HER2, KRAS G12C, Fusions and Later Lines
When the disease progresses on first-line treatment, the next choice is again made from the biomarkers, which is why the panel taken at diagnosis serves the whole treatment journey. A finding that changed nothing in the first line, such as a HER2 amplification, can decide the second or third. Where the first panel was narrow, comprehensive genomic profiling on the archived tissue is considered before the next line is chosen.
HER2 Amplification
In HER2-positive, RAS wild-type tumours, the MOUNTAINEER trial reported a 38 percent response rate with tucatinib plus trastuzumab in previously treated patients. The antibody-drug conjugate trastuzumab deruxtecan is another option in this group. HER2 amplification is also regarded as a marker of resistance to anti-EGFR antibodies.
KRAS G12C
A small subtype of KRAS mutation, G12C accounts for about 3 to 4 percent of colorectal cancers and is now targetable. In CodeBreaK 300, sotorasib with panitumumab, and in KRYSTAL-1, adagrasib with cetuximab, produced responses in previously treated patients. Guidelines place these combinations in later lines; inhibitors for other KRAS subtypes are in clinical trials.
NTRK and RET Fusions
Rare (under 1 percent) but important, because tumour-agnostic drugs such as larotrectinib, entrectinib and selpercatinib can be used. A broad NGS panel detects these fusions.
No Targetable Finding
Second-line FOLFIRI or FOLFOX with bevacizumab, ramucirumab or aflibercept, followed in later lines by trifluridine-tipiracil with bevacizumab, regorafenib or fruquintinib, all appear in the guideline. The order depends on which drugs were used first and on how well the patient tolerated them. How long each line runs, and when it is reviewed, follows the same logic set out for chemotherapy generally.
Where Circulating Tumour DNA Fits
Circulating tumour DNA (ctDNA) consists of fragments of tumour DNA shed into the bloodstream and analysed from a blood sample. ESMO's ctDNA recommendations accept a blood-based test as a valid alternative to tissue in metastatic disease when tissue is insufficient or a result is needed quickly. In practice, when tissue results would delay the first-line decision, a ctDNA test can provide the RAS and BRAF results sooner.
The second use of ctDNA is to monitor resistance mutations that emerge during anti-EGFR therapy; re-challenge with an anti-EGFR antibody after a break is considered when the blood shows no RAS mutation at that point. A negative blood result has a limit: when little tumour DNA is shed, an absent signal does not prove that the tumour is unchanged.
What This Means for a Patient Assessed in Türkiye
The bridge between a guideline and daily practice is drug licensing and reimbursement. Chemotherapy with bevacizumab, cetuximab and panitumumab has been in use for many years. The status of immunotherapy, encorafenib, tucatinib and KRAS G12C inhibitors in colorectal cancer differs by drug, changes over time and differs by country, in Türkiye as in the United Kingdom and the European Union; the position that applies to each patient in Türkiye is checked at the consultation for their own tumour profile. Where a drug is not licensed for the indication, an off-label application to the Turkish Medicines and Medical Devices Agency or referral to a clinical trial can be considered.
At Egepol Hospital in Izmir, the molecular results of every patient with metastatic colorectal cancer are reviewed by Prof. Dr. H. Ibrahim Petekkaya and the clinical molecular oncology team at the molecular tumour board, which matches the guideline sequence to the patient's data and issues a written recommendation. International patients can have this done as a remote document review before travelling; see the international patients page. Patients already on treatment elsewhere can have their plan checked through the second opinion service; the wider group of gastrointestinal cancers has its own overview.
Frequently Asked Questions
Which tests should every patient with metastatic colorectal cancer have?
Four results are needed at diagnosis: KRAS and NRAS (RAS) mutation status, BRAF V600E mutation status, mismatch repair or microsatellite instability status, and HER2 amplification. A broad NGS panel can add KRAS G12C subtype, NTRK and RET fusions for later lines. The results should be available before the first-line decision, ideally within about two weeks; if tissue is lacking or delayed, a circulating tumour DNA blood test is an accepted alternative.
Why does immunotherapy come before chemotherapy in MSI-high disease?
Mismatch repair-deficient tumours carry a very high number of mutations, which makes them visible to the immune system. In KEYNOTE-177, pembrolizumab alone outperformed chemotherapy as first-line treatment, and in CheckMate 8HW nivolumab plus ipilimumab reduced the risk of progression substantially compared with chemotherapy. Guidelines therefore place checkpoint inhibitors first for dMMR/MSI-high metastatic disease, with chemotherapy reserved for patients unsuitable for immunotherapy or after progression.
What is the first-line treatment for BRAF V600E colorectal cancer?
For fit patients with BRAF V600E-mutant, mismatch repair-proficient metastatic colorectal cancer, a BRAF-directed combination, encorafenib with cetuximab, added to FOLFOX chemotherapy is a preferred first-line option. In the BREAKWATER trial, adding encorafenib and cetuximab to FOLFOX improved the response rate and survival compared with chemotherapy alone. Patients who cannot tolerate chemotherapy may receive encorafenib and cetuximab without it. If the tumour is also dMMR/MSI-high, immunotherapy takes priority. Individual results vary.
Does it matter whether the tumour started on the left or the right side?
Yes. Left-sided tumours (descending colon, sigmoid and rectum) with RAS and BRAF wild-type status benefit clearly from anti-EGFR antibodies such as panitumumab or cetuximab added to chemotherapy, as the PARADIGM trial showed. In right-sided tumours that benefit has not been demonstrated, so chemotherapy with bevacizumab is preferred. Guidelines therefore combine sidedness with molecular results when choosing the first-line antibody.
What are the options for HER2-positive colorectal cancer?
HER2 amplification occurs in roughly 3 to 5 percent of metastatic colorectal cancers, mostly in RAS wild-type tumours. After chemotherapy, HER2-directed treatment is used: tucatinib with trastuzumab (MOUNTAINEER) and trastuzumab deruxtecan both appear in guidelines. HER2 amplification is also a marker of reduced benefit from anti-EGFR antibodies, which is one reason it is tested at diagnosis rather than only at progression.
I am already on treatment; does a guideline update change my plan?
Not automatically. A guideline summarises evidence; a plan that is working is not changed because a document was published. What an update does is prompt a check: have all four biomarkers been tested, and is the next line already mapped to the result? If a test is missing it can be run on stored tissue or on a blood sample. Whether a specific drug is available depends on licensing and reimbursement in the country of treatment.
Related Articles

How Many Chemotherapy Cycles Will I Have, and Who Decides?
Sayfayı Açın
What Does VUS Mean on an NGS Report, and How Do You Read the Rest of It?
Sayfayı AçınRelated Pages

Colorectal Cancer
Sayfayı Açın
Comprehensive Genomic Profiling
Sayfayı Açın
Immunotherapy
Sayfayı Açın
Targeted Therapy
Sayfayı Açın
Molecular Tumour Board
Sayfayı AçınSources and Guidelines
- Cervantes A et al. Metastatic colorectal cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up. Ann Oncol 2023;34(1):10-32. Link
- ESMO Clinical Practice Guidelines, gastrointestinal cancers: metastatic colorectal cancer guideline page, with the guideline and its published updates. Link
- NCCN Clinical Practice Guidelines in Oncology: Colon Cancer. Link
- Andre T et al. Nivolumab plus ipilimumab in microsatellite-instability-high metastatic colorectal cancer (CheckMate 8HW). N Engl J Med 2024;391:2014-2026. Link
- André T et al. Pembrolizumab in microsatellite-instability-high advanced colorectal cancer (KEYNOTE-177). N Engl J Med 2020;383:2207-2218. Link
- Kopetz S et al. Encorafenib, cetuximab and chemotherapy in BRAF-mutated colorectal cancer (BREAKWATER, response-rate analysis). Nat Med 2025;31:901-908. Link
- Watanabe J et al. Panitumumab vs bevacizumab added to standard first-line chemotherapy in left-sided RAS wild-type metastatic colorectal cancer (PARADIGM). JAMA 2023;329(15):1271-1282. Link
- Strickler JH et al. Tucatinib plus trastuzumab for chemotherapy-refractory HER2-positive RAS wild-type metastatic colorectal cancer (MOUNTAINEER). Lancet Oncol 2023;24(5):496-508. Link
- Fakih MG et al. Sotorasib plus panitumumab in refractory colorectal cancer with mutated KRAS G12C (CodeBreaK 300). N Engl J Med 2023;389:2125-2139. Link
- Pascual J et al. ESMO recommendations on the use of circulating tumour DNA assays for patients with cancer. Ann Oncol 2022;33(8):750-768. Link